Tuesday, 16 December 2014

Scheduled for Surgery? How to Go In Strong, Ready

5 steps to improve surgery outcomes

If you are waiting to have a scheduled surgery, you may not realize that there are things you should do in those days or weeks before to increase your chances of a successful outcome.

Source: From internet

Don’t simply wait for the scheduled date. Take these actions to be as healthy and strong as you can be, says general surgeon Kevin El-Hayek, MD. He offers patients these five tips:

1. Eat a “cleaner diet”

In the days before surgery, eat foods that are rich in vitamins and minerals. “I use the term, ‘cleaner diet,’ focused heavily on fruits and vegetables,” Dr. El-Hayek says. “We know that overall inflammation goes down when you eat foods rich in those respects.”
 Also, avoid processed foods, red meat and other foods which are more difficult to break down. ”As the body is preparing for a shock that’s coming up, avoiding those things will decrease inflammatory markers,” he says.


2. Exercise regularly

Among other benefits, getting more exercise in the weeks before a surgery will increase your chances of walking sooner after the surgery.
“Even if you’re not an athlete, patients can train their bodies during the weeks leading up to surgery,” says Dr. El-Hayek. Even something as simple as parking farther away from the door where you work or shop can help.
“Shoot for 5,000 to 10,000 steps a day to increase your stamina. The main thing is that, undoubtedly, one of the discharge criteria you’re going to have to meet before you go home is getting close to your preoperative level of activity,” he says.

Source: From internet

3. Kick bad habits

Use the time before surgery to quit smoking, stop drinking or using “any mood-altering substances that can affect your sleep or anxiety levels leading up to surgery,” Dr. El-Hayek says.
“Certainly in the few days leading up to surgery, alcohol and smoking can really affect the anesthesia.”
On the positive side, patients absolutely should engage in “meditation, prayer and things that are important to help people through the trauma that they’re about to undergo,” Dr. El-Hayek says.

Source: From internet

4. See your internist

If you have two weeks or more before surgery, it’s especially important to check in and let your doctor know what’s coming up.
“Your primary doctor might want to make changes in your medications to optimize surgery,” Dr. El-Hayek says. “Your blood pressure and blood sugar need to be well-controlled. From a wound-healing standpoint, the better the sugars are controlled, especially for diabetics, the better recovery you’re going to have.”
And he mentions one other reason: “Your primary care physician is going to be the one who sees you afterward, who is going to be managing the changes that happen due to surgery.”


5. Find out about supplements, vitamins

Be sure to ask your doctor about vitamins and supplements, because some of them can interact with other medications, particularly anticoagulants.
Medications that impact bleeding, such as aspirin, anti-inflammatory drugs (like Advil®), Plavix® and Coumadin® probably should be stopped, Dr. El-Hayek says.
“But these questions are addressed in the pre-op medical clearance appointment,” he says. “It really is the provider’s role to counsel patients on medication/supplement usage as this varies from patient to patient.”

Source: From internet


Source: Cleveland Clinic
Saturday, 29 November 2014

Constipation: 6 Ways to Unblock Yourself

You’re bloated and blocked. You strain on the toilet with no results — or with results that are painful. You’re constipated.
Constipation is common. Sometimes it stems from stress. Other times it comes from bad diet or lifestyle choices. Still other times, it’s brought on by a medical condition that requires a doctor’s attention.
You can find relief, though, whether your constipation is a typical case or something more serious. The difference comes in how you find relief.
Pic from  internet


1. Solutions are simple for most people

Most of the time constipation happens because you’re not eating the right foods, you’re not drinking enough water and you’re not exercising enough. So the fixes are straightforward: Move more, drink more water and add fiber to your diet to add bulk to your stool. Some of the patients have had success taking probiotics, too, to change the composition of the bacteria in the gut.
Pic from internet

2. Make time to move your bowels

This may sound simple, but people don’t always make bathroom time a priority. Try waking up earlier to eat breakfast and then move your bowels. Food can stimulate the need to go, and your home bathroom may be more relaxing. But don’t avoid public bathrooms when you feel the urge, either. Delaying a bowel movement can make constipation worse.
Pic from internet

3. Look to your plate

Have you made a major change in your diet? Sometimes drastic changes to what you eat can cause constipation. For example, if you suddenly cut all fat from your diet, it’s easy to get blocked up. This can occur in weightlifters who eat all protein, no fat. It can happen in people with eating disorders, too. You don’t want to overdo fat, but you need a little to move things through your bowel.

4. When to see a doctor

Sometimes simple changes are not enough. If your constipation is more than just a short-term bother, if it’s not responding to treatments and if it lasts for weeks, get yourself checked out to exclude more serious medical causes. Chronic constipation can be a sign of conditions such as hyperthyroidism, hypercalcemia, celiac disease or irritable bowel syndrome (IBS). It’s especially important to see a professional if you have other symptoms such as dizziness, fatigue, cramping or spasms.
Pic from internet

5. Fiber is not always the answer

Fiber works for most people, but not all. If fiber makes you more bloated and blocked than before, it could mean many different things. For example, in “slow transit constipation,” a condition where the bowel does not move things quickly through, fiber just sits there in your gut and can make you feel worse. Long story short: If fiber makes you worse, don’t just add more. Seek help.

6. If your constipation is serious, you have options

People with slow motility or IBS don’t have a cure for constipation, but you can treat it. There’s a wide range of laxatives available, plus pro-motility drugs that a doctor can prescribe. Sometimes at-home remedies can bring relief, too, including increasing dietary vegetable or mineral oil to lubricate the bowels. For people with celiac disease or wheat intolerance, cutting out gluten can make a world of difference.  
Here’s the bottom line: Try simple fixes first, but if they fail, don’t suffer needlessly. See a doctor — and find out what treatments can get your bowels moving again.


Source: Cleveland Clinic

Sunday, 16 November 2014

How You Can Deal With Anal Fissures

Anytime you have pain, bleeding and itching in your anal area, you’re going to worry.
First, these are all uncomfortable sensations — there’s no getting around that. And second, they can be scary and make you wonder, “What’s going on?”
Many patients will assume hemorrhoids are to blame, but there’s another common culprit behind symptoms such as these: anal fissures.
Anal fissures are small tears in the skin around your anus. They commonly cause itching and bleeding, and they tend to cause more pain than most types of hemorrhoids. When you have these symptoms, a doctor can help you get an accurate diagnosis — and the right kind of relief.

Risk factors — and how to lower them

Anal fissures can happen to just about anyone, but there are definitely factors that raise your risk. Constipation is a major one. Hard stool and straining on the toilet can put stress on your body and lead to these tears.
The same is true of diarrhea, even though it’s quite different from constipation. Anytime you have a change in your bowel habits that puts stress on your system, your risk goes up. That’s why we often see people come in with anal fissures after traveling, when changing diets put the digestive system to the test. Likewise, childbirth and the resulting stress on the body’s muscles and tissues can lead to fissures.
Fortunately, you can take preventive steps to lower your risk. They’re fairly simple:
  • Drink plenty of water. Hydration helps you avoid constipation.
  • Take an over-the-counter stool softener to avoid hard, dry bowel movements. Keeping things flowing through your body can help you avoid fissures. This is often good advice after childbirth in particular.
  • Watch your diet, and make sure you’re getting plenty of fiber and leafy greens. For protein, choose lean meats and fish over red meat. And don’t eliminate all fat from your diet, because fat and oil are good lubricants that keep your digestive tract functioning properly.


What to do if you have a fissure

First, a doctor will want to rule out hemorrhoids or other conditions with similar symptoms, as well as abscesses, infections or other more serious concerns.
Next, in conjunction with the lifestyle changes outlined above, treatment for a fissure usually starts conservatively with simple at-home fixes and conservative medical therapy.
At home: A “sitz bath” — soaking in warm, but not hot, water several times a day — works wonders for many patients. The pain many people feel before or right after a bowel movement comes from muscle spasms brought on by the anal fissure. Warm baths help those muscles relax, which in turn helps the fissure heal over time.
Medical management: Medical therapy targets the muscles, too. A doctor may offer an ointment that relaxes the anal muscles so the fissure can heal, minus the spasms. A numbing agent such as lidocaine is an option, too, but I tend not to use it because it can add to the burning and irritation.
Surgical options: When conservative treatments don’t work, there are two simple outpatient surgical options. One is a Botox injection into the anal muscles. This basically paralyzes the muscle to prevent spasms and allow the fissure to heal. The other option is sphincterotomy, a strategic cut to the muscle that also relieves spasms. Both come with a healing time of around two weeks.
The best option comes down to your individual needs. For example, a sphincterotomy has a slight risk of causing long-term bowel control issues, so it is not recommended for people who already have those issues. The same is true of people with Crohn’s disease or HIV, two groups with an increased risk of anal fissures. For these populations, Botox may be a better option if surgery is required.
The bottom line — is that you have plenty of options to treat this irritating condition. When you suspect an anal fissure, see a doctor to confirm those suspicions and find out which options are best for you.

Source: Cleveland Clinic


Tuesday, 4 November 2014

Your Colonoscopy: 7 Common Myths Debunked

Myth #1: “I’m not at risk for colon cancer.”

The truth is: Everyone is at risk, One in eighteen American men and women will get colon cancer in their lifetime. Adults above age 50 need to have a colonoscopy because the great majority of colorectal polyps – which are the precursors of colon cancer – occur after age 50. Removing polyps prevents colorectal cancer.


Myth #2: “If I don’t have any symptoms, I don’t need a colonoscopy.”

In nearly all cases, colon cancer starts as a precancerous growth in your colon, which usually doesn’t cause symptoms. A colonoscopy detects polyps so doctors can remove them before they turn into cancer. The idea is to do this before they cause symptoms. On average, endoscopists performing colonoscopies find precancerous polyps in 15 percent of women and 25 percent of men age 50 or over.


Myth #3: “There’s no way I can drink that prep stuff!”

Drinking a bowel preparation is one of the leading deterrents to having colonoscopy. The good news: Today’s bowel prep is easier than before. Rather than having to choke down a gallon of solution, patients can choose half-gallon options. What’s more, many physicians prescribe a split dose, where you take half the prep the night before and the other half on the morning of the procedure.


Myth #4: “A colonoscopy isn’t accurate.”

In 2008, a study reporting that colonoscopies may not completely protect against getting colon cancer gained a lot of media attention. But in that study, many colonoscopies were not complete and performed by general internists and family physicians who may not have had adequate experience to do the colonoscopy well.
More recent studies confirm that experience really matters when you choose who performs your colonoscopies. For a high quality colonoscopy, make sure your physician has specialized training in performing colonoscopies and tracks his or her outcomes as part of performance improvement.


Myth #5: “A colonoscopy is too painful!” or “I can’t be sedated enough.”

Actually, 99 percent of patients are adequately sedated through conscious sedation or twilight sleep and can be comfortable during their colonoscopy. Most patients don’t even remember the exam! Some hospitals also offer monitored anesthesia care for patients who require deeper sedation. 


Myth #6: “It’s too risky. My friend had his colon perforated during a colonoscopy.”

When performed by specially trained professionals, colonoscopies are extremely safe. The risk of perforation is less than 1 in 1,000 cases, and the risk of bleeding is less than 1 percent.

Myth #7: “If I get colorectal cancer, then it was meant to be.”

Not true. Colon cancer is preventable. Here’s how: Begin screening for colon cancer (colonoscopy is the preferred screening strategy) at age 50, or earlier if you have risk factors. Other things you can do: Improve your diet, maintain a normal body weight, exercise and avoid smoking.


Source: Cleveland Clinic

Friday, 24 October 2014

Diverticular Disease: Greatest Myths and Facts

Myth 1: If you have diverticular disease, you should avoid eating nuts, seeds and popcorn

Fact: This most persistent myth actually contradicts advice doctors give for preventing the condition in the first place. A healthy, high-fiber diet is actually the best medicine against diverticulitis, and seeds and nuts certainly fit the bill.
We used to think that a seed or nut plugged the pocket in the colon, and that’s what caused it to become inflamed or to rupture. But no surgeon has ever seen that, and studies have strongly suggested there’s nothing to that idea.


Myth 2: Diverticular disease always requires treatment

Fact: Patients often confuse the related conditions diverticulosis and diverticulitis.
Diverticulosis generally needs no treatment, while diverticulitis is a more serious condition that may require surgery.
Diverticulosis refers to small pockets that protrude through weak muscle layers in the intestinal wall, similar to a bubble in a tire. They’re fairly common. Sixty percent of people have them by age 60. Up to eighty percent of people have them by age 80.
A colonoscopy usually brings this condition to light, and it’s a very incidental finding. Most people don’t even realize they have the pockets, and by themselves, they are little cause for concern. Diverticulosis is like having freckles: It’s only a problem if those freckles turn into a mole. We don’t operate, ever, on diverticulosis.
Diverticulitis occurs when one or more of those pockets are blocked by waste and inflammation or an infection occurs, or when pockets rupture and bacteria that are normally in your stool get outside of the intestines and into the surrounding abdominal area.
When this happens, a variety of complications can arise:
  • You may experience pain and/or a fever.
  • An abscess, or “walled-off” infection, may result from the bacteria in the abdomen.
  • A painful infection of the abdominal cavity, or what we call peritonitis, occurs. Peritonitis is potentially fatal. Also, while it’s very uncommon, it does require immediate treatment.
Not everybody who has diverticulitis needs surgery, but they should see a physician, either in primary care or the emergency room, to get a proper diagnosis.


Myth 3: If you’ve had diverticulosis that developed into diverticulitis in the past, subsequent bouts of diverticulitis are more likely to perforate (and lead to peritonitis)

Fact: Diverticulitis happens in only 10 – 25 percent of those with diverticulosis. Also the great majority, or 75 percent, of those cases are the less serious type – requiring simple outpatient treatment, and perhaps medication.
Research shows the next bout of diverticulitis is most often going to be similar to your first bout. Usually, if your body could handle diverticulitis the first time, then the next time, it’s going to react just as well.
Lots of patients ask, “How do I prevent myself from getting diverticulitis?” Unfortunately, we don’t know why people get it. We think it’s from high pressure in the bowels and being constipated. We suggest eating a high-fiber, healthy diet and avoiding constipation.

Source: Cleveland Clinic

Monday, 20 October 2014

5 Facts You Should Know About Your Poops


There is no normal

People are different. So are bowel movements. The size, shape and consistency of feces will change greatly from person to person.
Instead of looking for “normal,” look for a change. Did you use to move your bowels frequently but now have trouble doing so? Did they use to be solid but now are runny for a long period of time? When you experience a big, noticeable change that lasts, it’s time to see your doctor.


Blood is a warning sign

If there is blood in your feces on a recurring basis, see a doctor. Blood can be a sign of polyps or colorectal cancer. It also can be caused by benign conditions such as hemorrhoids and anal fissures. In any case, it’s worth getting checked out.
If you see blood, keep an eye out for other symptoms: weight loss, fever, chills. When they come together, those are “high-alert” symptoms of bowel disorders.


Sometimes size is a concern

If you used to have sizeable stools but now they are always pencil thin and hard to pass, consult your doctor. In certain types of colon cancer, the bowel gets narrow, and so do your bowel movements.
Thin stools do not automatically mean cancer. But if they last a long time and if going to the bathroom is difficult for you, your doctor may order a colonoscopy to rule it out.

Consistency matters

We all have bouts of diarrhea from time to time. Runny, watery stool over a short period of time can mean mild food poisoning or an infection, for example.
But if you used to have solid bowel movements and now have diarrhea frequently, it could be a sign of an inflammatory bowel disease such as Crohn’s disease or ulcerative colitis — especially if it comes with other symptoms such as abdominal pain, blood and weight loss.

It could be stress

Your body reacts to things that go on around us. The impact of stress and unresolved issues may show up in your bathroom.
Your bowels may be indicating something that you’re not appreciating consciously. If your bathroom habits have changed drastically and other medical causes have been excluded, life’s stresses may be to blame.
Pay attention to what your bowels are telling you. From stress to medical conditions, they may give you warning sings that will help you improve your health.


Source: Dr Brooke Gurland, MD, Cleveland Clinic

Monday, 13 October 2014

Things You Need To Know About Fistula-in-ano

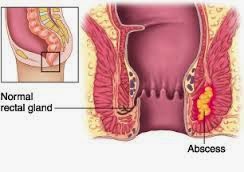
What Is An Anal Abscess?

An anal abscess is an infected cavity filled with pus found near the anus or rectum.


What Is An Anal Fistula (Fistula-in-ano)?

An anal fistula is frequently the result of a previous or current anal abscess. The small glands just inside the anus occasionally get clogged and potentially can become infected, leading to an abscess. The fistula is a tunnel that form under the skin and connects the infected glands to the abscess. A fistula can present with or without and abscess and may connect just to the skin of the buttocks near the anal opening. Other causes of fistula include Crohn's disease, tuberculosis, radiation, trauma and malignancy.


How Does Someone Get An Anal Abscess Or A Fistula?

The abscess is most often a result of an acute infection in the internal glands of the anus. Occasionally, bacteria, faecal material or foreign matter can clog the gland and create a condition for an abscess cavity to form.

After an abscess drains on its own or has been drained (opened), a tunnel (fistula) may persist connecting the infected anal gland to the external skin. This typically will involve some type of drainage from the external opening and occurs in up to 50% of the abscesses. If the opening on the skin heals when the fistula is present, a recurrent abscess may develop.


What Are The Signs And Symptoms Of An Abscess Or Fistula?

A patient with an abscess may have pain, redness or swelling around the anal area. Fever or chills are also common. In a patient with a fistula, there will be additional symptoms of irritation of the perianal skin or drainage from an external opening.


Is Any Specific Testing Necessary To Diagnose An Abscess Of Fistula?

No. Most of the abscesses or fistula are diagnosed and managed on the basis of clinical findings. Occasionally, a MRI or endoanal ultrasound can assist with the diagnosis of deeper abscesses or the delineation of the fistula tunnel to help guide treatment.


What Is The Treatment Of An Anal Abscess?

Surgical drainage is needed under most circumstances. An incision is made in the skin near the anus to drain the pus. It can be performed under local anaesthesia or general anaesthesia for bigger and deeper abscess. The wound would be left open and let it heal by itself. Hospitalisation may be required in patients prone to more significant infections such as diabetics or patients with decreased immunity.


What Is The Treatment Of An Anal Fistula?

Surgery is almost always necessary to cure an anal fistula. Although surgery can be fairly straightforward, it may also be complicated, occasionally requiring staged or multiple operations. It is advisable to consult a colorectal surgeon to discuss the different types of potential operations.

The surgery may be performed at the same time as drainage of an abscess, although sometimes the fistula does not appear until weeks to years after the initial drainage. If the fistula is straightforward, a fistulotomy may be performed. Other procedures include placing material within the fistula tract to occlude it or surgically altering the surrounding tissue to accomplish closure of the fistula, with the choice of procedure depending upon the type, length and location of the fistula.


What Is The Recovery Like From Surgery?

Pain after surgery is controlled with painkillers, fibers and bulk laxatives. Sitz bath is encouraged and to avoid constipation. You can discuss with your surgeon the specific care and time away from work prior to surgery to prepare yourself for post-operative care.


Can The Abscess Or Fistula Recur?

Yes. Both abscesses and fistulas can potentially recur. Should similar symptoms arise, suggesting recurrence, it is recommended that you visit a colorectal surgeon to manage your condition.


Source:ASCRS
